
Electrolytes and hydration: water, losses, and safety
How sodium, potassium, and water are distributed in the body, what EFSA guidelines mean, when a sports plan is necessary, and why ORS addresses a specific medical task. Human research and risks associated with kidney disease, medications, and excessive drinking.
Electrolytes have become a familiar word on sports bottles and water packets. They are marketed for energy, mental clarity, and recovery after any type of exertion, although the situations listed can have completely different causes. Sodium, potassium, and other ions are indeed essential: without them, the normal function of nerves, muscles, and fluid distribution is impossible. But the necessity of a substance does not mean that every person needs an additional mixture of it every day.
It is more useful to start with the objective: are we replenishing regular hydration, losses from sweat, consequences of diarrhea, or an established deficiency found in lab results? In these cases, the required amounts of water, salt, and carbohydrates differ, and sometimes medical attention is required. An oral rehydration solution is not a universal sports drink. Water from food and ordinary beverages also contributes to the balance, so popular volume-based recommendations are easily misinterpreted.
For a specialist, the topic begins with fluid distribution and regulatory mechanisms and ends with an evaluation of a specific product and patient. For the user, clear solutions are important: when is available drinking water and food sufficient, when is a plan for prolonged exertion necessary, and which symptoms should not be addressed with yet another packet. In both cases, a larger quantity does not necessarily provide a greater effect.
Ions, Water, and Interstitial Regulation
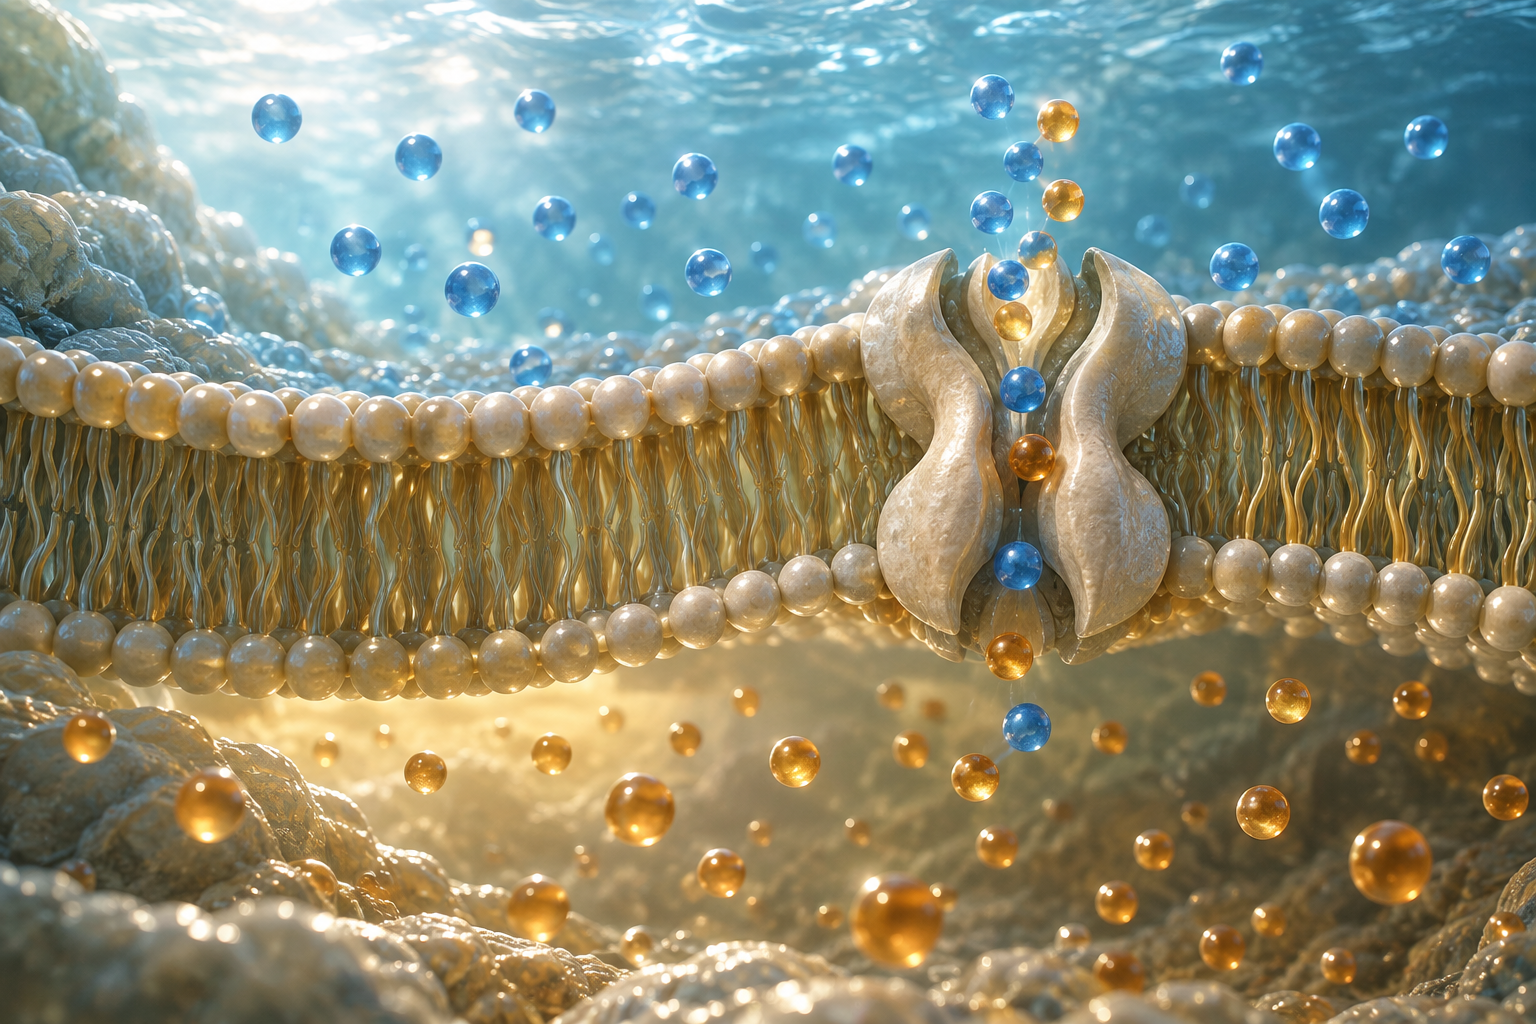
Electrolytes are substances that form charged particles in a solution. In physiology, the focus is primarily on sodium, potassium, chloride, as well as magnesium, calcium, and other ions with various functions. Sodium predominates in the extracellular space, while potassium is found inside cells. The difference in concentrations is maintained by active transport and is necessary for electrical signals and normal cellular function.
Water is distributed between cells, the interstitial environment, and the blood according to several forces. The osmotic effect depends on dissolved substances, while pressure and proteins also participate in fluid movement. Therefore, dehydration is not a simple state of "the body is low on sodium." One can lose water, salt, or various combinations of both, and blood concentrations will also reflect fluid distribution.
The kidneys regulate the excretion of water and ions by responding to signals regarding concentration and effective circulating blood volume. Vasopressin helps retain water, while the renin-angiotensin-aldosterone system participates in the regulation of sodium, potassium, and vascular tone. These mechanisms usually cope with daily fluctuations. However, disease, medications, significant losses, or excessive intake can alter the typical response.
This is precisely why blood sodium and dietary salt are not the same figure. Sodium concentration can decrease with an excess of water relative to dissolved substances, even if significant salt has been ingested. Edema also does not prove a simple deficit of an electrolyte drink: it can reflect various medical conditions. One cannot reliably prescribe a saline composition based on a single symptom.
Nerve and muscle function depend on ion gradients, but it does not follow that additional potassium will improve signaling in a person with a normal balance. Similarly, the participation of magnesium in enzymatic reactions does not prove that any mixture acts as a universal treatment for fatigue. Biological necessity and the effect of supplementation beyond normal intake are different questions. For clinical prescription, it is important to address a situation where a problem has actually been identified or an intervention has been studied.
The ion content in a product is also not equal to the mass of its salt. Sodium chloride contains sodium and chloride, and different magnesium compounds have an unequal proportion of elemental magnesium. At a professional level, it is the amount of the specific element and its form that are compared, rather than the number of milligrams associated with a fancy chemical name. This nuance explains many erroneous comparisons of powders.
For everyday practice, it is enough to remember that nutrition already provides electrolytes from various sources. Vegetables, legumes, dairy products, and other suitable foods can provide potassium and magnesium, while salt and prepared meals provide sodium. A packet is an additional intake that must be linked to a specific task. Without such a link, it simply changes the composition of the diet rather than automatically correcting a balance.
How Much Water: The Guideline Includes Food

The EFSA has established adequate total water intake guidelines of 2.0 L per day for adult women and 2.5 L for men under normal conditions. This is the total water from beverages and food moisture, not a requirement to drink an additional amount of pure water. These figures refer to population guidelines and moderate conditions. They do not set an invariable personal quota during heat, heavy exertion, or illness.
If a person obtains significant moisture from soups, fruits, and other foods, the contribution of beverages will differ from that in a drier diet. Therefore, the same number of glasses does not necessarily imply the same total intake. One should also not consider tea or other suitable liquids as completely "unaccounted-for water" simply because of their name. The composition of a drink influences dietary choices, but the water it contains remains part of the balance.
Thirst is an important physiological guide, although it is not always sufficient in specific situations. For an elderly person, in cases of certain diseases, or when one is unable to drink freely, an organized regimen may be required. This does not establish a general rule to force everyone to drink on a rigid schedule. The practical goal is the availability of liquid and compliance with conditions, not a competition in liters.
The color of urine sometimes helps to notice the direction of change, but it is not an accurate electrolyte analysis. It is influenced by the time of day, concentration, medications, and certain foods. There is no need to constantly strive for nearly colorless urine, and a single dark sample does not establish clinical dehydration. If symptoms are present, the assessment must take into account the overall state and possible causes.
Established fluid restrictions for heart or kidney failure cannot be overridden based on the general EFSA guideline. These patients represent a separate clinical situation where intake and output are regulated by an individual plan. Additional water or sodium may prove inappropriate. The usual recommendation for a healthy population does not replace a medical prescription.
Pregnancy, lactation, ambient temperature, and physical labor can change requirements. However, adding an electrolyte powder is not a mandatory consequence of any increase in water intake. The composition of one’s usual diet and the nature of losses also matter. One needs to understand exactly what is missing or what needs to be replenished, rather than purchasing a category based on a general symptom of fatigue.
A convenient habit is to have access to beverages and keep the usual regimen in mind without turning every sip into a complex calculation. For most domestic conditions, it is sufficient to combine liquid with a normal diet. If persistent intense thirst occurs, urination changes sharply, or other symptoms appear, the issue requires assessment. This may be a reason for seeking medical attention, rather than just choosing a more concentrated mixture.
Sweat losses and a plan for prolonged exertion

Sweat cools the body through evaporation and carries away water and electrolytes. The magnitude of losses varies with temperature, humidity, intensity, clothing, acclimatization, and individual characteristics. Sodium concentration is also not the same for everyone. Therefore, a single drink and one fixed rate of drinking cannot accurately replicate the losses of every participant.
The NATA position statement suggests individualizing the plan and assessing sweating in conditions similar to the actual activity. The approximate fluid loss is calculated from the difference in body mass before and after, adjusted for the amount drunk and urine voided. For example, a decrease of 0.6 kg with 0.4 L ingested and no urination corresponds to approximately a liter of loss during that period. This is an educational example, not a ready-made recommendation to drink that same volume immediately.
A one-time assessment does not describe all seasons and training sessions. During hot, prolonged work and a short, cool walk, the same person may have very different losses. It is better to repeat the observation under appropriate conditions and take into account the tolerability of the beverage. For sports, fluid availability, race logistics, and the ability to change the plan if the weather differs are important.
During prolonged or intense activity, carbohydrates and sodium in a beverage can perform different tasks. Carbohydrates provide fuel, sodium participates in replenishing losses and influences drinking properties, and water maintains balance. From an improvement in performance on a carbohydrate solution, one cannot attribute the entire result to electrolytes. Accurate comparison requires separate compositions and corresponding outcomes.
A short, standard workout does not automatically require a salt product. If losses are small and suitable food is subsequently available, regular drinking can cover the task without a special powder. But a professional plan for a multi-hour load has different goals and requirements. The boundary is determined by the circumstances, not by the presence of sportswear.
Sodium from a beverage should be accounted for in the total diet, especially if a person is already receiving a lot of salt or has a medical restriction. At the same time, a general preventive recommendation regarding salt should not mechanically override the replenishment of large athletic losses. These issues can coexist in an individual plan. It is important not to prescribe the same reduction or increase for everyone regardless of the context.
Exercise-associated muscle cramps are not a reliable at-home test for salt or magnesium deficiency. Muscle fatigue, the nature of the work performed, and other factors are possible causes, and recurring symptoms require evaluation. Given the mechanism of neuromuscular transmission, it is impossible to prove universal prevention by any mixture. A specialist’s task is to link the symptom to the conditions and exclude dangerous causes, rather than to assume a deficiency based on a marketing scheme.
Why excessive drinking is also dangerous

Exercise-associated hyponatremia occurs when the sodium concentration falls below normal in the relevant temporal context. One of the main causes is fluid intake that exceeds the body’s capacity to excrete it, especially with the persistent action of vasopressin. A person may drink with the good intention of "preventing dehydration" and yet still increase their risk. Therefore, a safe strategy must prevent not only deficiency but also excess.
The 2015 International Consensus emphasizes the role of excessive fluid consumption and the use of thirst as an important limiter. Sodium in a sports drink does not guarantee protection if a person continues to drink too much. Such drinks are usually significantly less concentrated in sodium than plasma. The risk of excess water cannot be corrected simply by adding another salt tablet.
Changes in body mass during activity help to identify potential excessive intake, although it is not the only diagnostic criterion. If weight increases during prolonged exertion due to drinking, it is a reason to revise the plan rather than to consider the result an ideal replenishment. At the same time, weight changes involve other processes, so an accurate clinical assessment requires context. One cannot determine sodium concentration based on weight alone.
Headache, nausea, weakness, and deterioration of condition can occur with various problems. If there is an impaired level of consciousness, significant confusion, or severe symptoms after exertion, urgent medical attention is required. Continuing to force-feed water without understanding the cause is unsafe. Field advice to "drink more" does not replace a differential assessment.
This risk does not mean that one should restrict drinking to a minimum under all conditions. Insufficient replenishment during heat and work can also worsen one's condition. The correct goal is proportionality to real losses and the ability to respond to conditions. A plan based on individual observations and physiological signals is better than a universal command to drink a specific large volume every hour.
Education is particularly important at mass-participation events where water is available in several locations and participants are afraid to miss a station. Greater accessibility does not mean an obligation to drink at every point. The organizer and medical team must explain both sides of the balance. Such an approach helps to avoid the false notion that prevention is always equal to the maximum possible fluid intake.
For the reader, one practical conclusion is useful: electrolytes do not turn an excessive volume into a safe one. The composition of the drink and the quantity are independent parameters. If alarming symptoms appear, a new dose of powder should not be considered a diagnostic experiment. Timely assistance is more important than trying to guess on your own which ion is currently needed.
Oral rehydration for diarrhea is a separate task

During diarrhea, water and electrolytes are lost, and the composition and magnitude of these losses may differ from those of sweat. An oral rehydration solution (ORS) is designed for this specific medical task. It utilizes the preserved transport of sodium together with glucose across the intestinal epithelium, which aids water absorption. The presence of glucose here is functional and is not equivalent to the usual role of a sugary drink.
The standard low-osmolarity formula of the WHO and UNICEF contains 75 mmol/L of sodium and glucose, and the total osmolarity is 245 mOsm/L. These numbers describe the specified solution, not a universal sports concentration. The formula also includes other components. To prepare it, one must use the appropriate packet and the precise indicated volume of safe water.
Too little water changes the concentration; too much dilutes the composition; adding juice or sugar creates a different solution. Therefore, one should not "improve" a pharmacy packet to suit one's taste or divide an unknown portion of powder by eye. The instructions are part of the application. For a professional recommendation, it is important to consider the specific product, age, and degree of loss.
A sports drink, sweet soda, and water with a pinch of salt are not automatically equivalents of ORS. They may differ in sodium, glucose, and osmolarity, and the objective of performance does not overlap with the treatment of diarrheal dehydration. Even an attractive list of minerals does not confirm the necessary medical composition. Comparisons should be based on formula and indication, not on the word "electrolytes."
The WHO views dehydration as a key danger and indicates that intravenous assistance may be required in severe cases or shock. An inability to drink, pronounced lethargy, and other alarming signs require assessment, especially in a child. A solution does not automatically eliminate all causes of diarrhea. Volume and strategy depend on the clinical condition.
Glucose in a medical solution should not be excluded due to the general trend to reduce free sugars. However, the presence of a proven transport mechanism does not provide grounds for drinking ORS daily "for the cells." The benefit of the treatment arises in a specific situation of loss and need. Under normal conditions, extra sodium and energy may simply be excessive intake.
It is practically important to distinguish a home first-aid kit from a sports shelf in advance. If a product for rehydration has been purchased, its purpose and instructions must be preserved; if it is a sports mixture, it should not be considered a treatment for a disease. Recurring intestinal losses require identifying the cause. This clarity protects against two errors: refusing the necessary glucose in ORS or using a medical formula where the task is entirely different.
Potassium and magnesium: normal function does not negate clinical risks

Potassium is essential for the electrical stability of cells, but a concentration that is too high in the blood can be dangerous for the heart. Regulation depends, among other things, on the kidneys and medications. The NIH ODS reviews the increased risk in chronic kidney disease and with drugs that reduce potassium excretion. Therefore, "potassium for the heart" is not a sufficient explanation for a prescription.
ACE inhibitors, angiotensin receptor blockers, and potassium-sparing diuretics are particularly important. Their benefit under appropriate indications does not negate the need to account for additional potassium. Salt substitutes, powders, and several supplements may provide it simultaneously. A patient should not independently change a medication or add a concentrated source based on general advice.
Dietary potassium and medical correction of deficiency solve different tasks. A normal diet can support intake with appropriate foods, but confirmed hypokalemia requires an assessment of the cause and strategy. Conversely, in the case of kidney disease, restrictions are individualized: one cannot automatically ban all plants or permit any supplement. Analyzes, the stage of the disease, and the entire treatment plan matter.
In the SSaSS study, 20,995 participants from 600 villages in China used ordinary salt or a mixture of 75% sodium chloride and 25% potassium chloride. Over an average of 4.74 years, the incidence of stroke was lower with the substitute: a rate ratio of 0.86. However, people with serious kidney disease or those taking drugs that significantly raise potassium were excluded. Therefore, the lack of an apparent increase in serious hyperkalemia in the study does not guarantee safety for these specific patients.
Magnesium is involved in a multitude of reactions, yet the symptom of fatigue does not allow for the establishment of its deficiency. The NIH ODS material describes sources, forms, and risks of supplements, including diarrhea and problems with impaired excretion. Different salts are not equal in their share of elemental substance and tolerability. Additional diarrhea can itself complicate the task of hydration.
Combining several minerals in one sachet does not automatically make the doses balanced for everyone. A person with a sodium restriction, another with a risk of hyperkalemia, and an athlete with significant losses represent different cases. The presence of a substance in the body does not establish the need for an additional amount. A recommendation must explain the purpose of each significant component.
If weakness, palpitations, pronounced stool disturbances, or other symptoms are recurring, an assessment is required, rather than the sequential purchase of increasingly concentrated mixtures. Analyzes may be significant, but they are interpreted together with the clinical situation. One should neither prescribe testing for everyone based on fatigue alone nor consider a powder a substitute for diagnostics. The boundary between a food product and medical correction must remain clear.
How to choose a beverage and not confuse the outcomes

On the label, one should first look at the amount of sodium, potassium, and other components in the portion actually consumed. Then, one should evaluate the carbohydrates, energy, stimulants, and dilution instructions. Numbers per liter and per measuring scoop cannot be compared without the final volume. An attractive name like "isotonic" does not automatically describe the necessary clinical formula or the benefit for a specific task.
In a study by Maughan et al., 72 normally hydrated men drank a liter of water or a selected beverage over half an hour, after which their urine was measured. Some options, including ORS and milk, provided greater short-term fluid retention; the ORS index after two hours was about 1.54 relative to water. This is a laboratory outcome at rest. It does not mean a 54% improvement in athletic performance or that everyone needs to drink a medical solution daily.
Less urine is not always equivalent to better health. In that specific experiment, the metric helped compare short-term balance, but it did not test long-term safety, fatigue management, or heat illness. Similarly, palatability, which makes drinking easier, is a useful property in some conditions and may contribute to excess in others. Interpretation depends on the goal, not on a single top-ranked winner.
For an ordinary day without large losses, accessible drinks and sufficient nutrition are more practical. For prolonged sports, a plan accounting for sweat and tolerance is needed; in cases of diarrhea, appropriate rehydration and severity assessment are required. If an electrolyte imbalance is established, the choice is determined by the clinical cause. These scenarios are best distinguished in advance so that the same word on a package does not replace different tasks.
If a powder is used, it is important to observe dilution and not combine multiple products without understanding the total quantities. An energy drink with caffeine may have a completely different nutritional role, even if it contains sodium. A concentrated potassium supplement is not equal to a regular beverage with a low content. The form, dose, and purpose remain the primary characteristics.
Specific restrictions on fluids, sodium, or potassium must be maintained during travel and training. They should not be abandoned for general advice about heat; an individual plan must provide for such conditions in advance. In case of severe symptoms, the task is not to choose the ideal flavor. Timely assistance and an understanding of the likely cause are needed.
Electrolytes become easier to understand when they cease to be a universal answer to any malaise. Water from food is accounted for, losses vary, ORS has a specific medical function, and excessive drinking can also cause harm. This knowledge allows one to choose fewer random products and be better prepared for real circumstances. An additional mixture is useful when its composition and quantity correspond to the task.
FAQ
Should I drink 2–2.5 L of pure water on top of food?
No. EFSA guidelines include water from beverages and food. Requirements change during heat, physical activity, and illness, and an individual plan applies when fluid restriction is prescribed.
Do I need electrolytes after every workout?
Not necessarily. Duration, losses, conditions, and food intake after activity are more important. The plan for multi-hour activity differs from a short, standard workout.
Can ORS be used as a daily sports drink?
It is designed for medical rehydration, primarily for diarrhea. Its formula, concentrations, and purpose differ from sports fuel or regular beverages. There is no universal need to take ORS daily.
Does salt protect me if I drink too much water?
No. Sodium in a sports drink does not make excessive fluid volume safe. Severe symptoms after activity require medical help, not more salt or forced drinking.
Is potassium beneficial for everyone's heart?
It is essential, but extra potassium can be dangerous if you have kidney disease or take certain medications. You must account for all sources, including salt substitutes, and not take concentrated supplements based on general advice.
Does a cramp mean a magnesium deficiency?
A single cramp is not enough to diagnose a deficiency. Various causes exist, including activity conditions and muscle fatigue. Recurrent or severe symptoms require evaluation instead of random mineral supplementation.
Sources
- EFSA. Scientific Opinion on Dietary Reference Values for water (2010)
- WHO and UNICEF. Oral rehydration salts: production of the new ORS (2006)
- WHO. Diarrhoeal disease: dehydration and treatment
- McDermott et al. National Athletic Trainers' Association Position Statement: Fluid Replacement for the Physically Active (2017)
- Hew-Butler et al. Third International Exercise-Associated Hyponatremia Consensus (2015)
- Maughan et al. A randomized trial to assess beverages and hydration status: development of a beverage hydration index (2016)
- NIH Office of Dietary Supplements. Potassium: Health Professional Fact Sheet
- NIH Office of Dietary Supplements. Magnesium: Health Professional Fact Sheet
- Neal et al. Effect of Salt Substitution on Cardiovascular Events and Death (2021)